qEEG in Frontotemporal Dementia and Alzheimer’s Disease: Can Brain Electrical Activity Help Differentiate the Two?
 Frontotemporal dementia and Alzheimer’s disease can sometimes look surprisingly similar in clinical practice.
A patient may present with memory difficulty, reduced initiative, behavioural change, impaired judgement, language problems or executive dysfunction. As neurodegenerative illnesses progress, their clinical features may overlap even further.
Yet the underlying patterns of brain dysfunction are not identical.
One intriguing question is whether quantitative electroencephalography, or qEEG, can help identify these differences.
A study by Lindau and colleagues published in Dementia and Geriatric Cognitive Disorders examined this question by combining qEEG measurements with detailed neuropsychological testing in people with frontotemporal dementia (FTD) and Alzheimer’s disease (AD).
The findings are particularly interesting because they suggest that FTD and Alzheimer’s disease may show different patterns of electrical slowing—and that combining electrophysiology with cognitive testing may be more useful than either approach alone.
Why Distinguishing FTD From Alzheimer’s Disease Matters
Frontotemporal dementia and Alzheimer’s disease are both neurodegenerative disorders, but their early clinical presentations often differ.
The paper describes early and middle-stage FTD as predominantly characterised by behavioural disturbances, whereas Alzheimer’s disease is more commonly associated with deficits involving:
- memory
- visuospatial abilities
- language
Personality may initially remain relatively preserved in Alzheimer’s disease, although these distinctions become less obvious as both illnesses progress.
Imaging patterns also differ.
The authors note that FTD is typically associated with abnormalities involving the frontal and anterior temporal regions, while Alzheimer’s disease more characteristically involves the hippocampal, medial temporal and parietotemporal regions.
But structural and functional imaging are only part of the picture.
Electrical brain activity may provide another window into how these illnesses affect brain networks.
What Is qEEG?
A routine EEG records spontaneous electrical activity generated by the brain.
Traditional EEG interpretation relies heavily on visual inspection by an experienced clinician.
Quantitative EEG goes a step further.
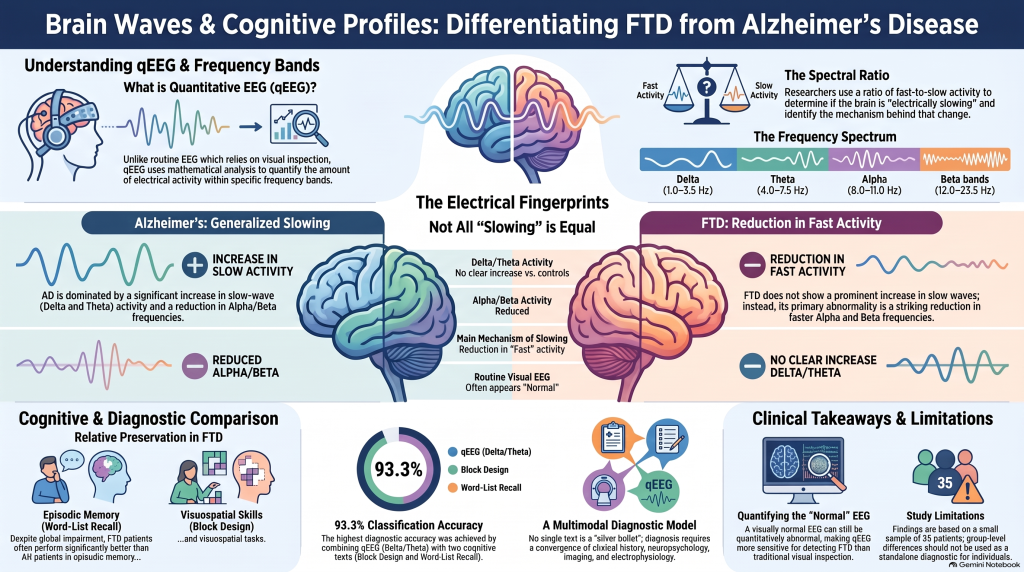
The electrical signal is mathematically analysed so that the amount of activity occurring within different frequency bands can be quantified.
In this study, the researchers analysed six frequency ranges:
- Delta: 1.0–3.5 Hz
- Theta: 4.0–7.5 Hz
- Alpha: 8.0–11.0 Hz
- Beta-1: 12.0–15.5 Hz
- Beta-2: 16.0–19.5 Hz
- Beta-3: 20.0–23.5 Hz
They also calculated a spectral ratio comparing faster EEG activity with slower EEG activity.
Conceptually, this allowed the researchers to ask:
Is the brain becoming electrically slower?
And importantly:
Is that slowing occurring in the same way in Alzheimer’s disease and frontotemporal dementia?
The answer appeared to be no.
The Study
The researchers examined three groups:
- 19 people with frontotemporal dementia
- 16 people with Alzheimer’s disease
- 19 healthy control participants
The patient groups were broadly matched for demographic characteristics and overall cognitive severity as measured by the MMSE.
Participants underwent extensive assessment.
The patients had received clinical examination, neuropsychological testing, EEG and brain imaging including MRI, CT and SPECT. EEG recordings were obtained close to the time of neuropsychological testing.
For EEG analysis, recordings were performed while participants were awake, resting and had their eyes closed.
Artifact-free EEG epochs were selected and analysed using frequency-domain techniques.
The Central qEEG Finding
The most important finding can be summarised quite simply:
Alzheimer’s disease showed substantially more slow-wave activity.
Frontotemporal dementia showed relatively less slow-wave increase, but reductions in faster activity.
This distinction is central to understanding the paper.
qEEG Pattern in Alzheimer’s Disease
The Alzheimer’s disease group demonstrated a pattern of generalised EEG slowing.
Delta activity was significantly increased compared with both the FTD group and healthy controls.
Theta activity was also higher in Alzheimer’s disease than in FTD, although its difference from controls was less clear.
Alpha activity was reduced compared with healthy controls, and higher-frequency beta-2 and beta-3 activity was also lower.
Overall, the spectral ratio showed considerably greater slowing in Alzheimer’s disease than in either FTD or healthy controls.
A simplified representation is:
Alzheimer’s disease → increased slow activity + reduced faster activity → greater overall EEG slowing
This fits with the broader observation discussed by the authors that increased slow-frequency activity has long been recognised as a characteristic EEG finding in Alzheimer’s disease.
qEEG Pattern in Frontotemporal Dementia
The FTD pattern was different.
Compared with healthy controls, people with FTD did not show a clear increase in delta or theta activity.
Instead, the more striking abnormality was a reduction in faster EEG activity.
Alpha and beta activity tended to be reduced relative to healthy controls.
The authors summarised the FTD pattern as:
- no prominent increase in slow delta/theta activity
- reduction in faster alpha and beta frequencies
In contrast, the Alzheimer’s pattern was dominated more strongly by increased slow activity.
This is clinically interesting because conventional EEG had historically often been described as relatively normal in FTD.
The study suggested that quantitative analysis might detect abnormalities that are not obvious on routine visual inspection.
A Useful Concept: Not All EEG “Slowing” Is the Same
One of the most interesting observations in the study concerns the spectral ratio.
Both FTD and Alzheimer’s disease could show a reduction in the ratio of fast-to-slow EEG activity.
But the mechanisms appeared different.
In FTD, the reduced ratio was primarily produced by:
reduction of faster frequencies
whereas in Alzheimer’s disease, it was more strongly related to:
increase in slower frequencies.
The authors explicitly highlight this distinction.
This is an important principle when interpreting qEEG.
A single summary number showing “slowing” does not necessarily tell us what produced that slowing.
Two patients could have similar overall ratios for very different electrophysiological reasons.
Examining individual frequency bands therefore remains important.
Why Might Alzheimer’s Disease Produce More Slow-Wave Activity?
The study itself does not establish a mechanism.
However, the authors observed that pathology involving parietal regions, as commonly seen in Alzheimer’s disease, appears to be particularly well reflected in EEG slowing.
They also discuss earlier work suggesting that increasing theta activity may appear in milder Alzheimer’s disease and increasing delta activity may become more prominent with greater disease severity.
The critical point is that the study demonstrated a stronger slow-frequency signature in the AD group than in the FTD group.
It did not establish that a particular frequency abnormality represents a specific pathological process in an individual patient.
Neuropsychology Was Equally Important
The researchers did not examine EEG in isolation.
They also performed a battery of neuropsychological tests assessing:
- attention
- concentration
- executive-attentional performance
- visuospatial abilities
- short-term memory
- episodic memory
- semantic knowledge
- abstract thinking
Tests included Digit Symbol, Trail Making Tests A and B, Block Design, clock tasks, Digit Span and word-list learning measures.
The cognitive findings were striking.
FTD Patients Performed Better Than AD Patients in Several Domains
Compared with the Alzheimer’s disease group, the FTD group showed relatively better performance in:
Attention and processing
FTD patients performed better on Digit Symbol and Trail Making measures.
Visuospatial functioning
They performed better on Block Design and clock reading.
Episodic memory
Free recall of a word list was better in FTD than in Alzheimer’s disease.
The statistically significant differences reported included Digit Symbol, Trail Making A, Trail Making B, Block Design, clock reading and word-list free recall.
Importantly, this does not mean that cognition was normal in FTD.
The authors point out that even the comparatively better-performing FTD group showed substantial impairment compared with expected performance in healthy individuals.
Their argument was about relative preservation, not absence of cognitive dysfunction.
That distinction is extremely important.
qEEG Alone Was Not the Best Diagnostic Tool
Perhaps the most clinically responsible finding of the entire study is that qEEG alone did not provide the strongest differentiation.
The authors explicitly state that although there were clear group-level EEG differences:
qEEG alone did not differentiate FTD and Alzheimer’s disease particularly well.
Neuropsychological testing on its own actually performed better than individual qEEG measures in some analyses.
This is important because it argues against treating qEEG as a standalone diagnostic test for dementia subtype.
Instead, the most promising approach was multimodal.
The Best Results Came From Combining qEEG and Neuropsychology
The investigators constructed statistical models combining electrophysiological and cognitive variables.
Their best-performing model included:
- delta activity
- theta activity
- Block Design performance
- word-list free recall
This combination produced a reported 93.3% classification accuracy for distinguishing the FTD and Alzheimer’s disease groups within this particular study sample.
The authors considered this combination particularly clinically useful because it brought together:
- relative absence of prominent slow-wave increase in FTD
- relatively preserved visuospatial abilities
- relatively preserved episodic memory
The same model achieved the paper’s highest reported classification accuracy.
But this figure deserves careful interpretation.
It came from a small research sample consisting of only 35 dementia patients.
It should therefore not be interpreted as meaning that qEEG plus two cognitive tests can diagnose FTD versus Alzheimer’s disease with 93% accuracy in routine clinical practice.
It demonstrates the potential value of combining modalities—not a validated universal diagnostic algorithm.
Conventional EEG Versus qEEG in FTD
Another interesting finding concerns conventional EEG.
Historically, visually interpreted EEG was frequently described as normal or relatively preserved in FTD.
In fact, the paper notes that older diagnostic descriptions had even considered a relatively normal conventional EEG to be supportive of frontotemporal degeneration.
Yet quantitative analysis in this study detected systematic alterations, particularly reductions in faster frequencies.
The authors therefore proposed that qEEG may be more sensitive than visual EEG inspection for detecting electrical abnormalities associated with FTD.
That is an important distinction:
A visually normal EEG is not necessarily a quantitatively normal EEG.
What Did the Study Actually Find?
A practical summary looks like this:
| Feature | Frontotemporal Dementia | Alzheimer’s Disease |
|---|---|---|
| Delta activity | No clear increase vs controls | Increased |
| Theta activity | No clear increase vs controls | Higher, particularly vs FTD |
| Alpha activity | Reduced | Reduced |
| Beta activity | Reduced, particularly compared with controls | Some higher-frequency beta reduction |
| Overall slowing | Present but less pronounced | More pronounced |
| Main mechanism behind spectral slowing | Reduction in fast activity | Increase in slow activity |
| Episodic memory | Relatively better preserved | More impaired |
| Visuospatial performance | Relatively better preserved | More impaired |
| qEEG alone | Limited differentiation | Limited differentiation |
| Best approach in this study | qEEG + neuropsychology | qEEG + neuropsychology |
These are group-level research findings, not rules for diagnosing an individual patient.
Why Neuropsychological Testing Matters So Much in Dementia
The paper reinforces an important principle in cognitive assessment:
The diagnosis of dementia should not depend on a single screening score.
Two people could obtain similar MMSE or MoCA totals while having fundamentally different neuropsychological profiles.
One patient might predominantly show:
- episodic memory impairment
another:
- executive dysfunction
another:
- visuospatial dysfunction
another:
- behavioural disinhibition
another:
- language impairment
The pattern of cognitive dysfunction frequently matters more than the global score alone.
This study illustrates that principle well.
The FTD and AD groups had broadly similar global cognitive impairment, yet their detailed neuropsychological performance differed substantially.
qEEG Should Be Interpreted in Context
The study does not support using an isolated EEG frequency abnormality to label a patient as having Alzheimer’s disease or FTD.
Instead, qEEG potentially adds another layer to clinical formulation.
A meaningful dementia assessment may therefore integrate information from multiple levels:
Clinical phenotype
What changed first: memory, personality, language, behaviour, executive ability or visuospatial functioning?
Collateral history
What has the family observed over time?
Neuropsychological profile
Which cognitive domains are disproportionately affected and which are relatively preserved?
Neurological examination
Are there motor, extrapyramidal, frontal-release or other neurological findings?
Structural imaging
What is the pattern of cerebral atrophy?
Functional or molecular investigations where appropriate
Does additional imaging or biomarker testing support a particular neurodegenerative process?
Electrophysiology
Does conventional EEG or qEEG provide useful complementary evidence?
This approach is conceptually consistent with the authors’ conclusion: detailed neuropsychological assessment and instrumental investigations such as qEEG should be considered alongside clinical diagnostic criteria.
Important Limitations of the Study
The paper is scientifically interesting, but several limitations should temper clinical interpretation.
1. Small sample size
There were only:
- 19 FTD patients
- 16 Alzheimer’s disease patients
- 19 controls
Small samples increase the possibility that impressive classification results will not reproduce with the same accuracy in larger populations.
2. This Was a 2003 Study
The diagnostic frameworks used in the study reflected the standards available at the time.
Modern dementia assessment has subsequently incorporated newer clinical criteria, advanced imaging and increasingly sophisticated molecular biomarkers.
Therefore, this paper is best understood as an important piece of the historical and scientific development of quantitative EEG in dementia rather than as a modern standalone diagnostic protocol.
3. Group Differences Are Not Individual Diagnoses
A statistically significant difference between groups does not mean every individual with FTD has one EEG pattern and every individual with Alzheimer’s disease another.
Considerable biological overlap can exist.
4. EEG Was Not a Localization Study
The study used global field power.
The authors explicitly point out that this method measures generalised EEG amplitude and does not itself identify where the EEG generators originate.
Therefore, the paper should not be interpreted as demonstrating precise cortical localisation from the qEEG recordings.
The Larger Lesson: Dementia Is a Pattern, Not a Number
This study illustrates something more important than whether delta, theta or beta activity changes.
Dementia diagnosis emerges from convergence of evidence.
No single MMSE score diagnoses Alzheimer’s disease.
No single neuropsychological deficit diagnoses FTD.
No isolated MRI finding provides the complete clinical picture.
And no single qEEG abnormality should be interpreted as a dementia biomarker in isolation.
The most useful information emerges when clinical history, behavioural phenotype, cognitive architecture, imaging and electrophysiology are interpreted together.
That is exactly where the Lindau study becomes conceptually valuable.
The best differentiation in their sample did not come from qEEG alone.
It came from combining brain electrical activity with neuropsychological performance.
qEEG and Neuropsychology: Complementary Rather Than Competing Tools
Neuropsychological assessment asks:
What is the brain struggling to do?
qEEG asks a different question:
What patterns of electrical activity accompany that dysfunction?
Structural imaging asks:
Where has the brain changed anatomically?
Clinical history asks:
How has the person changed in real life?
These are different levels of information.
The future value of cognitive assessment is unlikely to come from replacing one with another.
It is more likely to come from intelligently integrating them.
Clinical Takeaway
The Lindau study suggests a potentially useful electrophysiological distinction between Alzheimer’s disease and frontotemporal dementia.
Alzheimer’s disease was characterised predominantly by increased slow-frequency EEG activity.
FTD showed comparatively little slow-wave increase but more prominent reduction in faster activity.
At the same time, FTD patients demonstrated relatively better preservation of episodic memory and visuospatial abilities than the Alzheimer’s disease group.
Most importantly, the strongest differentiation emerged when qEEG findings and neuropsychological results were considered together, rather than when either was used independently.
The study therefore provides an early illustration of a principle that remains highly relevant to cognitive neuroscience:
Complex neurodegenerative disorders are best understood through patterns across multiple domains—not by searching for one diagnostic number.
Reference
Lindau M, Jelic V, Johansson SE, Andersen C, Wahlund LO, Almkvist O. Quantitative EEG Abnormalities and Cognitive Dysfunctions in Frontotemporal Dementia and Alzheimer’s Disease. Dement Geriatr Cogn Disord. 2003;15:106–114.